How does decompression surgery relieve spinal canal stenosis?
How is spinal canal stenosis diagnosed?
3 Qs
Spinal Tumours & Vertebral Trauma Reconstruction
How are unstable high-energy burst fractures surgically stabilized?
What is the surgical goal when resecting spinal tumours?
8 Qs
Spine Deformity, Scoliosis & Pediatric Correction
How does German surgical training influence complex deformity correction?
How is sagittal balance evaluated in adult spinal deformity?
2 Qs
Surgical Precision, Pre-Op Planning & International Patient Care
How does pre-operative planning ensure precision in spine surgeries?
How is multi-clinic care coordinated across Dubai, Egypt, and Germany?
Featured Medical Answers
Primary Neurosurgical Procedures & Care Guidance
Direct clinical guidance formulated in accordance with international spine surgery standards.
Expand All Answers
01Can herniated discs heal naturally without surgery?
Yes, many herniated discs undergo resorption and heal within 6 to 12 weeks with conservative care, physical therapy, and target pain management.
02How are unstable high-energy burst fractures surgically stabilized?
Unstable traumatic burst fractures are managed through canal clearance and percutaneous or open pedicle screw fixation across adjacent intact levels, restoring load-bearing mechanics and spinal alignment.
03How does decompression surgery relieve spinal canal stenosis?
Microscopic or endoscopic bilateral decompression removes thickened ligamentum flavum, facet joint overgrowths, and disc bulges through a unilateral approach, freeing compressed spinal nerves without compromising vertebral stability.
04How does German surgical training influence complex deformity correction?
German clinical protocols emphasize three-dimensional vertebral derotation, micro-precise osteotomies, and continuous intraoperative multimodal neuromonitoring (IONM) to achieve maximal structural realignment while preserving spinal cord and nerve root integrity.
05How does microscopic discectomy ensure nerve safety?
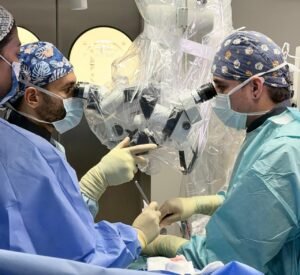
Microdiscectomy utilizes a surgical microscope offering up to 20x magnification and coaxial illumination. This provides crisp visualization of the dura, traversing nerve roots, and disc fragments, enabling selective removal of only the herniated tissue.
06How does pre-operative planning ensure precision in spine surgeries?
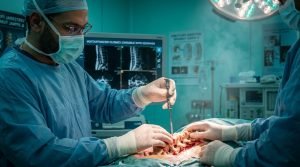
Advanced pre-operative protocols combine multi-slice 3D CT reconstructions, dynamic flexion-extension radiographs, and software modeling to plan precise screw trajectories, osteotomy cut angles, and customized implant sizing.
07How is multi-clinic care coordinated across Dubai, Egypt, and Germany?
Patients benefit from integrated care pathways featuring initial in-clinic or teleconsultation reviews, unified diagnostic standards, execution of advanced surgical interventions across accredited international hospitals, and synchronized post-operative follow-up.
08How is sagittal balance evaluated in adult spinal deformity?
Evaluation involves full-spine standing radiographs to assess spino-pelvic parameters, matching Pelvic Incidence to Lumbar Lordosis (PI-LL ≤ 10°), Sagittal Vertical Axis (SVA), and pelvic tilt to ensure stable, fatigue-free upright standing.
09How is spinal canal stenosis diagnosed?
Diagnosis combines clinical symptoms—such as neurogenic claudication (leg heaviness and aching relieved only by bending forward or sitting)—with high-resolution MRI scans confirming circumferential narrowing of the spinal canal.
10How is surgical stability achieved during major revision spine reconstructions?
Rigidity is restored by anchoring multi-rod configurations across healthy cranial vertebrae down to the sacrum and pelvis using S2-alar-iliac (S2AI) or iliac screws, paired with extensive microscopic neurolysis.
11How is thoracic kyphosis treated when curvature becomes severe?
When thoracic kyphosis exceeds 50° to 60° due to Scheuermann's disease or structural wedging, surgical management employs posterior Ponte or Smith-Petersen osteotomies combined with dual-rod instrumentation to restore global sagittal balance.
12How long does a microscopic lumbar microdiscectomy take?
The procedure usually takes between 45 and 90 minutes. It is performed under general anesthesia with microscopic magnification to ensure absolute nerve safety.
13How quickly can a patient walk following endoscopic discectomy?
Patients are typically mobilized within 2 to 3 hours after surgery and discharged on the same day with negligible tissue soreness.
14Is pediatric scoliosis surgery safe?
Yes, using modern intraoperative neuromonitoring and dynamic tensioning cords makes the procedure exceptionally safe and motion-preserving.
15What are the clinical risks of untreated kyphoscoliosis?
Untreated dual-plane kyphoscoliosis can lead to rigid trunk collapse, severe restrictive lung disease, reduced thoracic volume, premature cardiopulmonary compromise, and progressive neurological compression.
16What are the primary advantages of Minimally Invasive Spine Surgery (MISS)?
MISS accesses spinal pathologies through microscopic or tubular dilators without stripping paraspinal muscles, resulting in up to 80% less blood loss, significantly reduced post-operative pain, minimal scarring, and same-day or 24-hour discharge.
17What constitutes a surgical emergency in spinal disc disorders?
Cauda Equina Syndrome is a true medical emergency, presenting with sudden bowel or bladder dysfunction, saddle anesthesia (numbness in the groin/perineal area), and rapidly progressing bilateral leg weakness or foot drop.
18What defines complex or revision spine surgery?
Revision procedures address complications from previous operations, including pseudoarthrosis (failure of bone fusion), implant loosening or breakage, adjacent segment disease (ASD), flatback syndrome, or persistent post-surgical scar tissue compression.
19What indicates the need for scoliosis correction surgery rather than conservative management?
Surgical intervention is typically indicated when spinal curvature exceeds 40° to 50° on the Cobb angle scale, or when progressive deformity compromises pulmonary function, creates trunk imbalance, or causes intractable chronic pain refractory to bracing and physical therapy.
20What is full-endoscopic spine surgery?
An ultra-minimally invasive technique performed through an incision of approximately 7 to 8 mm using a high-definition endoscope under continuous saline irrigation, allowing disc removal and decompression with minimal bone or ligament disruption.
21What is sciatica, and what causes it?
Sciatica refers to sharp, shooting pain traveling along the sciatic nerve pathway—from the lower back, through the buttock, and down the back of the leg to the foot—typically provoked by mechanical compression or chemical inflammation from a herniated lumbar disc.
22What is spondylolisthesis and how is it treated?
Spondylolisthesis occurs when one vertebra slips forward over the one beneath it due to pars defects or degenerative facet laxity. Moderate to severe unstable slips are treated with spinal realignment, neural decompression, and interbody fusion.
23What is the difference between ACDF and Cervical Artificial Disc Replacement (ADR)?
Anterior Cervical Discectomy and Fusion (ACDF) removes the damaged disc and fuses the adjacent vertebrae with a cage. Artificial Disc Replacement (ADR) replaces the disc with a mobile implant, preserving full neck rotation and protecting adjacent levels from future stress.
24What is the recovery timeline for Dynamic Scoliosis Correction (VBT)?
Most young patients can sit and walk on day 1 post-op. Light sports can resume in 6 weeks, and full unrestricted physical activity is typical by 12 weeks.
25What is the surgical goal when resecting spinal tumours?
The primary objectives are achieving complete oncological tumor clearance (via en bloc spondylectomy or debulking), immediate decompression of the spinal cord, and 3D anterior column reconstruction using expandable titanium or carbon-fiber cages.
26What is Vertebral Body Tethering (VBT), and how does it differ from traditional spinal fusion?
VBT is a non-fusion, dynamic growth-modulation technique that stabilizes the spine using flexible biocompatible cords attached to anterior vertebral screws. Unlike rigid posterior fusion, VBT preserves natural spinal flexibility and allows continued skeletal growth.
27What non-surgical interventions exist for chronic back and neck pain?
28What solutions are available for pediatric patients with early-onset scoliosis?
For children under the age of 10, modern protocols utilize growth-friendly systems, including Magnetically Controlled Growing Rods (MCGR), which allow non-invasive outpatient rod lengthening every few months without repeated open operations.
Degeneration progresses from initial disc desiccation (loss of hydration) and annular fissuring to disc bulging, and ultimately focal rupture of the annulus fibrosus with nucleus pulposus extrusion (disc herniation).
30What symptoms signal cervical disc disease?
Sharp pain radiating from the neck across the shoulder down to the arm and fingers (cervicobrachialgia), accompanied by tingling, loss of fine finger dexterity, or weakness when lifting or gripping objects.
31When is Balloon Kyphoplasty recommended for vertebral fractures?
Balloon Kyphoplasty is indicated for acute, painful osteoporotic compression fractures that fail conservative immobilization. It restores collapsed vertebral height and provides immediate pain relief via targeted bone cement (PMMA) augmentation under local anesthesia.
32When is non-surgical conservative treatment prioritized for disc herniations?
Over 80% to 85% of disc herniations resolve within 6 to 8 weeks through targeted anti-inflammatory medications, selective transforaminal epidural injections, and structured spine physiotherapy, avoiding surgery unless progressive nerve deficits emerge.
33Which spinal levels are most susceptible to lumbar disc herniation?
The L4-L5 and L5-S1 segments bear the highest biomechanical torque in the human body, making them the most frequent sites for herniations that cause sciatic nerve root compression.
34Who is an ideal candidate for dynamic scoliosis correction (VBT)?
Skeletally immature children and adolescents (typically Sanders stage 2–4 or Risser grade 0–2) with flexible idiopathic thoracic or lumbar curves measuring between 40° and 65°.
No questions found matching your search criteria.
Show All Questions
Patient FAQs & Clinical Information: FAQs
What are the advanced spine treatment options by Dr. Hazem ElFezary?
Dr. Hazem ElFezary specializes in state-of-the-art scoliosis correction, microscopic discectomy, posterior spinal fusion, and endoscopic spine procedures.
The content provided is for educational and informational purposes only and does not substitute for a formal clinical consultation and X-ray evaluation with Dr. Hazem ElFezary, Consultant Spine Surgeon.